Heart Catheterization Explained: Prep, What to Expect, Recovery, and Essential Safety Facts

Over one million Americans enter a cardiac catheterization laboratory each year to investigate unexplained chest tightness, abnormal stress tests, or acute heart attacks. Despite being one of the most routinely performed vascular evaluations in modern cardiology, the prospect of lying conscious on an imaging table while a cardiologist threads a flexible tube toward your coronary arteries prompts understandable dread. Clinical guidelines and pre-admission protocols, like those detailed in the PeaceHealth Report, emphasize that thorough preparation dramatically cuts procedural complications and eases patient anxiety.
Understanding the mechanics of the test changes the experience entirely. Rather than a blind surgical intervention, a heart cath procedure functions as a high-definition vascular map, allowing interventional cardiologists to pinpoint arterial narrowing, calculate intracardiac pressures, and immediately transition from diagnostic evaluation to lifesaving arterial clearance.
📌 Key Takeaways:
- Core Purpose: Evaluates severe coronary artery disease via live fluoroscopy imaging and direct arterial pressure monitoring.
- Access Shift: Over 85% of diagnostic caths now prioritize transradial access in the wrist to slash bleeding complications.
- Actionable Prep: Strict pre-procedure fasting rules and targeted medication pauses protect kidney function and prevent aspiration.
- Recovery Window: Radial entry lets patients sit up within 15 minutes, while femoral puncture requires hours of rigid immobility.
How the Cath Lab Transforms Diagnostic Cardiology
The modern catheterization suite looks less like an operating room and more like an industrial imaging cockpit. Large, pivoting C-arms glide silently over the procedure table, delivering low-dose X-ray beams through fluoroscopy imaging systems that record heart movement at 15 to 30 frames per second.
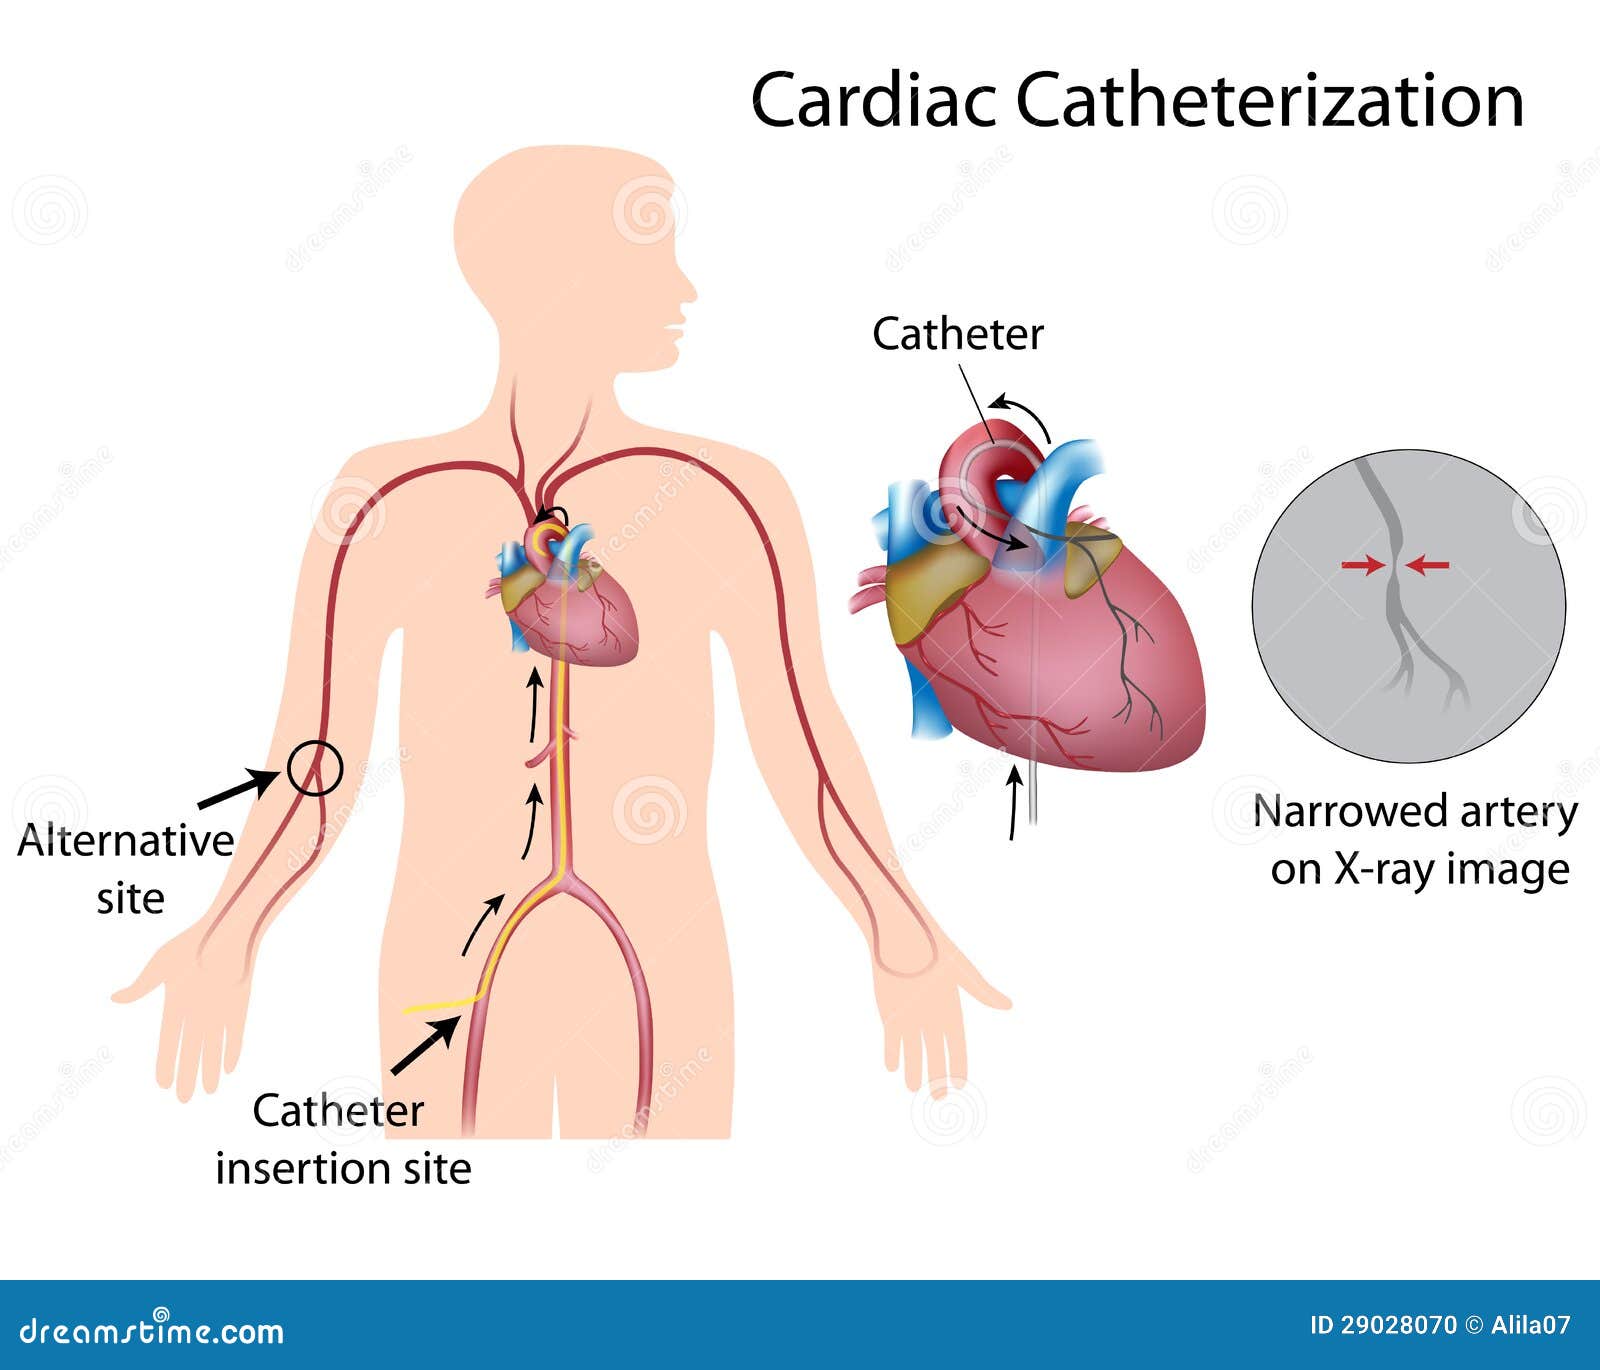
When patients arrive with symptoms pointing toward advanced coronary artery disease, non-invasive stress tests and echocardiograms only provide functional clues. A coronary angiogram delivers anatomical certainty. Once the physician places a long sheath into an access artery, they navigate pre-shaped diagnostic catheters up the vascular tree into the roots of the left and right coronary arteries.
Direct contrast dye injection makes translucent arterial lumina instantly visible against the X-ray screen. Cardiologists search for plaque buildup, calcified lesions, and vessel tortuosity. If an artery exhibits more than 70% narrowing, or if an unstable blockage cuts off blood supply during an active myocardial infarction, the diagnostic session evolves on the spot. The operator runs a microscopic guidewire through the catheter, inflates an angioplasty balloon to compress the lipid core, and deploys a drug-eluting cobalt-chromium stent to hold the vessel wall open permanently.
Pre-Procedure Fasting Rules and Medication Adjustments
Safe catheterization starts at home at least 24 hours before the patient steps onto the hospital floor. Clinical teams issue strict pre-procedure fasting rules, demanding no solid foods for at least 6 to 8 hours prior to admission. Clear fluids are typically restricted within 2 hours of check-in. This protocol protects the airway. If conscious sedation causes mild nausea or triggers a vasovagal drop in blood pressure, an empty stomach prevents gastric contents from entering the lungs.
Medication reconciliations require equal precision:
Anticoagulants and antiplatelet drugs (such as warfarin, apixaban, or clopidogrel) demand strict timing adjustments. Physicians balance the danger of acute thrombosis against bleeding risks at the puncture site. Patients managing type 2 diabetes must hold metformin for 48 hours following iodinated contrast exposure to avoid contrast-induced acute kidney injury and lactic acidosis. Daily insulin doses are typically halved on the morning of the procedure to prevent hypoglycemia while fasting.
Kidney function blood panels (BUN and serum creatinine) are mandatory checkpoints. Because the radiographic contrast agent filters through renal tubules, patients with pre-existing renal impairment receive targeted intravenous hydration with normal saline before and after the scan to flush the kidneys.
Radial Artery Access Versus Femoral Artery Puncture
For decades, the standard entry point was a femoral artery puncture in the right groin. While the femoral artery provides a wide, direct highway to the ascending aorta, it carries notable downsides: elevated bleeding rates, retroperitoneal hemorrhage risks, and mandatory prolonged bed immobility. Over the last decade, high-volume centers migrated overwhelmingly to transradial access through the wrist.
Access Pathway:
Radial Artery (Wrist) ──► Brachial Artery ──► Subclavian ──► Ascending Aorta ──► Coronary Ostia
Femoral Artery (Groin) ──► External Iliac ──► Common Iliac ──► Abdominal Aorta ──► Ascending Aorta
Choosing the wrist over the groin fundamentally alters the post-operative trajectory. Wrist entry allows nurses to achieve rapid hemostasis using a targeted mechanical compression band (like a TR Band), liberating the patient to walk and eat almost immediately.
| Clinical Variable | Radial Artery Access | Femoral Artery Puncture |
|---|---|---|
| Major Bleeding Rate | 0.5%, 1.2% | 2.0%, 4.5% |
| Mandatory Bed Rest | 0, 15 minutes | 2, 6 hours flat on back |
| Puncture Site Compression | Pneumatic wrist pressure band | Vascular closure plug or manual groin clamp |
| Vascular Complications | Radial spasm, superficial bruising | Retroperitoneal bleed, pseudoaneurysm |
| Average Same-Day Discharge | 2, 4 hours post-procedure | 4, 8 hours (or overnight stay) |
Groin access remains essential when patients present with small, calcified radial arteries, previous coronary artery bypass grafts requiring tortuous catheter angles, or clinical scenarios requiring large-bore mechanical circulatory support devices like an intra-aortic balloon pump.
What Conscious Sedation Actually Feels Like
General anesthesia is rarely used during heart catheterizations. Instead, clinical teams use conscious sedation, typically combining short-acting intravenous midazolam and fentanyl.
The goal is anxiolysis and analgesia without respiratory depression. You remain awake, capable of answering verbal questions, taking deep breaths on command, or coughing to clear dye from coronary channels when instructed.
The procedure begins with a sharp sting from a 1% lidocaine injection to numb the skin around the wrist or upper thigh. You feel pressure, tapping, and dull movement as the sheath enters the vessel, but the interior lining of human blood vessels lacks pain receptors. Catheters navigating your internal vasculature generate no tactile sensation.
When the physician injects contrast dye into the coronary branches or the left ventricle, a wave of systemic warmth rolls over the body. It lasts 20 to 30 seconds. Patients frequently describe this sensation as a sudden hot flash traveling from the chest through the pelvis. It is a harmless chemical reaction caused by the high osmolarity of the contrast agent expanding peripheral capillaries.
Managing Hematoma Risks and Recovery Timelines
Once catheters are withdrawn, the spotlight shifts to site stabilization and hematoma risks. An uncontrolled arterial puncture can bleed rapidly under systemic blood pressures, creating a hard, painful lump of coagulated blood within surrounding subcutaneous tissue.
For wrist procedures, nursing staff gradually deflate the pneumatic band over 90 to 120 minutes. Patients can sit upright, drink fluids, and use the restroom almost immediately. Discharge paperwork usually clears within three hours if no stenting took place.
Groin procedures require strict post-procedure bed rest. Patients must lie flat on their backs with their leg kept dead straight for 2 to 6 hours. If the cardiologist used an automated closure device (such as an extravascular collagen plug or suture anchor), bed rest shrinks toward the 2-hour mark. If mechanical manual pressure was used to seal the femoral artery, bed rest stretches to 6 hours to prevent the initial platelet plug from shearing open. Sneezing, coughing, or lifting the head during this phase spikes intra-abdominal pressure and can trigger sudden femoral site re-bleeding.
Overall heart cath recovery time spans 3 to 7 days before resuming normal baseline activities:
- Day 1, 2: Remove dressing; wash the site gently with mild soap and warm water. Pat dry; do not submerge in a bathtub, pool, or hot tub.
- Day 3, 5: Refrain from pushing, pulling, or lifting items heavier than 10 pounds. Avoid strenuous aerobic workouts, cycling, or sexual activity.
- Return to unrestricted desk work and moderate exertion, provided the access site shows no active swelling, expanding bruising, or discharge.
Frequently Asked Questions (FAQ)
Q1: Will I feel pain when the stent opens inside my heart?
A1: Stent deployment can cause momentary chest tightness or pressure lasting 10 to 15 seconds while the inflated balloon temporarily blocks coronary blood flow. It fades the instant the balloon deflates, leaving the metallic mesh anchored securely against the vessel wall.
Q2: What should I do if my puncture site begins bleeding at home?
A2: For radial wrist bleeding, apply hard, direct thumb pressure directly over the skin puncture and slightly above it while elevating your arm over your heart. For groin bleeding, lie completely flat, push down firmly on the puncture site with stiff fingers, and call 911 immediately. Never attempt to drive yourself to the emergency department.
Q3: How much radiation exposure happens during an angiogram?
A3: Diagnostic coronary angiography exposes patients to an average effective dose of 2 to 5 millisieverts (mSv), roughly comparable to 1, 2 years of natural background radiation. Advanced catheterization labs use digital pulsed fluoroscopy to minimize scatter and exposure while preserving image quality.
Q4: Why can't I drive myself home after the procedure?
A4: Conscious sedation medications compromise reaction times, spatial judgment, and neuromuscular coordination for up to 24 hours. Applying sudden pressure on a brake pedal can also disrupt fresh arterial seals in femoral or radial access points.
Navigating Your Cath Lab Discharge Safely
Leaving the outpatient cardiac floor with clear findings, or an newly placed coronary stent, demands attentive self-monitoring. Bruising the size of a silver dollar is common, but expanding firm masses, red streaks, localized warmth, or cold, pale extremities require immediate evaluation by the on-call interventional cardiology team.
If your angiogram revealed severe multi-vessel disease requiring bypass surgery (CABG) or if it concluded cleanly with conservative medical management, the procedure delivers clarity. By following basic preparation guidelines, understanding sedation, and honoring physical restrictions during the first week of healing, you minimize vascular hazards and let the diagnostic data work for your long-term cardiovascular health.


