Ozempic vs. Zepbound: Fact-Checking Serena Williams' Weight Loss Medication Confession
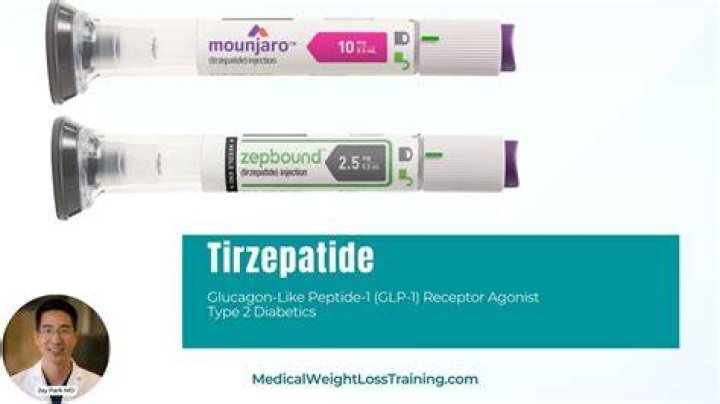
When Serena Williams appeared in early 2026 showing a noticeably leaner silhouette, social media feeds instantly defaulted to the generic cultural shorthand of our era: Ozempic. The assumption spread across TikTok and X within hours. Yet the viral chatter missed the critical clinical reality behind her transition. According to investigative coverage from a verified Yahoo Sports Report, Williams did not take Ozempic; she turned to Zepbound, the dual-action GIP and GLP-1 receptor agonist manufactured by Eli Lilly.
The distinction matters far beyond brand names. As Williams spoke openly to national broadcasters about managing her body composition after stepping away from professional tennis, her disclosure crossed two separate cultural wires: the ongoing mainstreaming of clinical anti-obesity drugs and an escalating debate over metabolic conditioning in competitive athletics.
📌 Quick Summary:
- The Medication: Reporting confirms Williams was prescribed Zepbound (tirzepatide), not Ozempic or Wegovy (semaglutide).
- The Post-Tour Driver: After her 2022 retirement, systemic inflammation, chronic joint strain, and shifted metabolic output made elite-level conditioning unsustainable through diet and exercise alone.
- The Athletic Fallout: Williams stated the therapy left her feeling healthier than during her competitive prime, prompting sports scientists and anti-doping officials to debate whether these therapies represent medical recovery or functional enhancement.
How the Ozempic Rumor Collided With Clinical Reality
The public tendency to label every visible Hollywood or athletic slim-down as an "Ozempic body" stems from Novo Nordisk’s early market dominance. Semaglutide, approved under the brand names Ozempic for type 2 diabetes and Wegovy for chronic weight management, captured global headlines in late 2022. By early 2024, the brand name had become a generic verb, much like Xerox or Kleenex.
That colloquial habit misdiagnosed Williams’ actual regimen. Eli Lilly’s Zepbound operates on a different pharmacological pathway. While semaglutide acts strictly as a GLP-1 receptor agonist, tirzepatide stimulates both glucose-dependent insulinotropic polypeptide (GIP) and glucagon-like peptide-1 (GLP-1) receptors. Clinical data from the SURMOUNT trials showed that this dual agonism yields higher average reductions in total body mass, often exceeding 20% to 25% of baseline weight, compared to roughly 15% typically observed with semaglutide.
When sports commentators seized on her appearance, they recycled the dominant catchphrase. The clinical reality was that Williams chose a newer dual-incretin peptide designed to address metabolic resistance that resisted conventional physical conditioning.
Retirement Realities and the Metabolic Shift After 27 Years on Tour
Elite professional tennis demands an extreme metabolic expenditure. At her competitive peak, Williams trained between four and six hours daily, cycling through plyometrics, on-court sprint drills, and heavy resistance training. That routine burned thousands of calories each day while simultaneously masking underlying insulin dynamics and chronic joint inflammation.
Stepping away from professional competition in late 2022 abruptly removed that extreme caloric furnace. Williams addressed this post-career fitness transformation directly, discussing how her body rebelled once tour-level volume ended. High-impact athletes frequently encounter intense rebound effects upon retirement. Tendon microtrauma, damaged cartilage, and years of anti-inflammatory injections often make sustained high-intensity interval training excruciating.
Williams explained that despite maintaining sensible nutrition, her metabolic baseline stalled. Post-pregnancy hormonal shifts, combined with the sudden drop in daily cardiovascular volume, left her fighting metabolic resistance that conventional training could no longer solve. For an athlete whose muscular, powerful frame had endured scrutiny for decades, acknowledging the biological difficulty of post-tour weight maintenance brought an unexpected layer of vulnerability to her public profile.
Clinical Comparison: Tirzepatide Versus Semaglutide in High-Performance Bodies
Understanding why an elite athlete would be prescribed tirzepatide over older GLP-1 compounds requires looking directly at the pharmacology, dosing schedules, and body composition data recorded across clinical trials.
| Clinical Parameter | Zepbound (Tirzepatide) | Ozempic / Wegovy (Semaglutide) |
|---|---|---|
| Manufacturer | Eli Lilly | Novo Nordisk |
| Target Receptors | Dual GIP & GLP-1 receptor agonist | Selective GLP-1 receptor agonist |
| Mean Weight Reduction | 20.9%, 25.3% (SURMOUNT-1 data) | 14.9%, 16.0% (STEP-1 data) |
| Lean Muscle Mass Preservation | Higher retention ratio when paired with progressive resistance load | Documented risk of sarcopenia without high protein protocols |
| Average Monthly List Price (US, 2026) | $1,059 (without commercial savings cards) | $968, $1,349 (depending on formulation) |
| Primary Gastrointestinal Risk | Nausea, mild diarrhea, delayed gastric emptying | Nausea, vomiting, constipation, reflux |
For former power athletes, lean mass retention is paramount. When high-performing individuals drop significant weight rapidly, losing muscle tissue can destabilize previously repaired joints. Tirzepatide’s dual mechanism appears to deliver more favorable fat-to-muscle loss ratios when combined with deliberate strength regimens, making it a frequent clinical pick for former professional athletes managing long-term musculoskeletal damage.
The Controversial Confession: Feeling Healthier Off Court Than on Tour
The comment that sent shockwaves through sports media arrived when Williams spoke with NBC News. She acknowledged that this medical weight loss intervention left her feeling healthier than she did while hoisting Grand Slam trophies. The statement challenged the traditional romance surrounding elite sport.
We often treat professional athletics as the gold standard of human wellness. Sports medicine specialists know the opposite is frequently true. Competing at the highest levels of tennis is fundamentally catabolic. Tour life involves systemic exhaustion, chronic ibuprofen use, cortisone therapies, sleep disruption across time zones, and persistent pain.
Williams explained that shedding visceral weight through targeted incretin therapy relieved long-standing pressure on her knees, ankles, and lumbar spine. Her resting cardiovascular metrics stabilized. Blood biomarkers associated with systemic inflammation dropped. By decoupling her daily existence from the punishing demands of pro conditioning, the medication provided metabolic balance that two decades of world-class physical output could never sustainably deliver.
The Performance Enhancement Debate Reaches Sports Medicine
The athletic world listened carefully to Williams' remarks. Within weeks, an analysis in The Athletic explored the broader question facing modern sports: Are GLP-1 and dual GIP/GLP-1 receptor agonists emerging as functional performance enhancers?
Currently, the World Anti-Doping Agency (WADA) does not include semaglutide, tirzepatide, or any GLP-1 analogues on its prohibited substance list. They are not anabolic steroids, nor do they mimic erythropoietin (EPO) to boost oxygen capacity. Yet their ability to manipulate body composition while preserving cardiovascular capacity has captured the attention of coaches across weight-class disciplines, endurance cycling, and tennis.
Consider the potential athletic advantages: rapid shedding of non-functional adipose tissue, suppressed appetite during demanding training blocks, and improved insulin efficiency. Conversely, exercise physiologists highlight real dangers for active competitors. Delayed gastric emptying can trigger severe intra-match bonking. Glycogen depletion risks spike during multi-hour matches. Dehydration from gastrointestinal side effects can lead to muscle tears or heat illness.
Williams addressed these medications as a retired icon addressing personal metabolic health, not an active competitor gaming a weigh-in. Still, her high-profile transparency accelerated conversations inside regulatory bodies. Sports governing boards are already weighing whether these medications should carry therapeutic use exemptions (TUEs) or face monitoring lists for active tour participants.
Frequently Asked Questions (FAQ)
Q1: Why did people believe Serena Williams was taking Ozempic?
Public culture often uses "Ozempic" as an umbrella phrase for any noticeable pharmaceutical weight drop. Because Novo Nordisk's drug entered the public consciousness first, casual observers and social media users assumed Williams had taken it, even though medical records and subsequent reporting confirmed she used Eli Lilly’s Zepbound.
Q2: How does Zepbound differ chemically from Ozempic?
Ozempic uses semaglutide, which acts solely as a GLP-1 receptor agonist to curb appetite and regulate glucose. Zepbound uses tirzepatide, a dual-action compound that activates both GIP and GLP-1 receptors. That dual agonism typically produces greater average body-weight reductions in clinical trials.
Q3: Are active professional tennis players allowed to take GLP-1 medications?
Yes. As of 2026, WADA does not classify GLP-1 receptor agonists or dual GIP/GLP-1 therapies as banned performance-enhancing drugs. However, the international tennis integrity bodies and sports medicine federations are actively reviewing their potential impact on weight management and physiological recovery.
Q4: Can everyday patients expect identical results to Serena Williams?
Outcomes vary considerably across individual metabolic baselines. While clinical trials show substantial average body weight decreases on tirzepatide, Williams paired her medical therapy with elite-tier strength maintenance, professional nutritional support, and personal trainers, which shielded her from the significant muscle wasting sometimes seen in unmonitored patients.
Rethinking Athletic Bodies After the Final Match
Williams’ decision to speak candidly about Zepbound signals an important shift in how society views athletic longevity. For decades, retired sports legends retreated behind closed doors to deal with post-career weight fluctuations, joint decay, and metabolic slowdowns, often carrying unfair public criticism for failing to maintain impossible competitive standards.
By confirming her use of a dual-incretin medication and correcting the record on Ozempic, Williams pushed metabolic science into the mainstream sports discourse. Her disclosure reminds us that an elite athlete's body is still a human biological system, vulnerable to the same hormonal and metabolic resistance that affects anyone else. Her experience demonstrates that reaching lasting wellness after retirement often requires modern clinical medicine, rather than relying solely on the grueling discipline that defined a hall-of-fame career.


