What Early Staph Looks Like: Key Visual Indicators and Skin Warning Signs
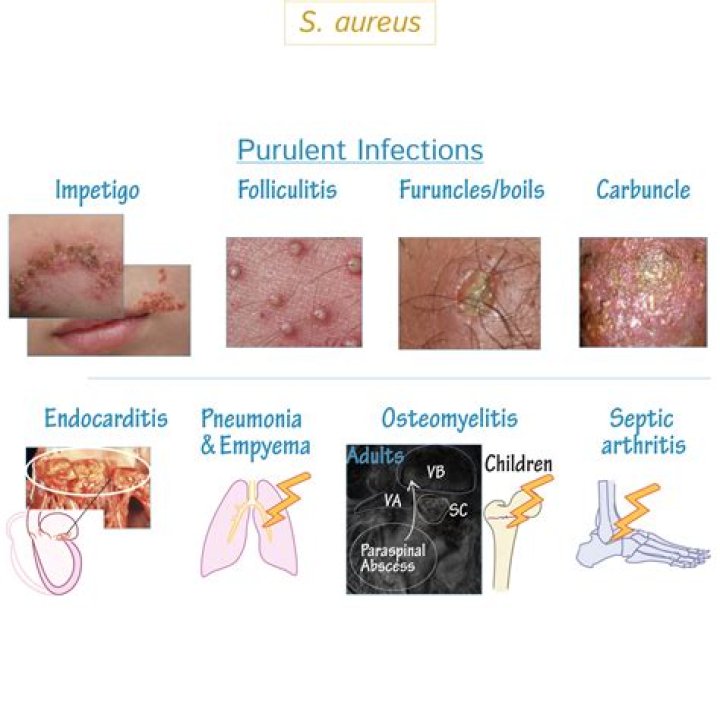
A tiny pimple appears on your forearm after a morning workout. Within twelve hours, that minor blemish throbs with noticeable heat, ringed by a perimeter of tightening, tender skin. Most people reach for over-the-counter hydrocortisone, assuming they have encountered an aggressive mosquito or an ingrown hair. That miscalculation often grants Staphylococcus aureus the head start it needs to breach deeper subcutaneous tissue. Clinical guidance highlighted in a recent Prevention Report reveals that identifying visual indicators in the initial twenty-four hours makes the difference between a simple topical salve and an emergency surgical drainage procedure.
Roughly thirty percent of the global population naturally carries staph bacteria in their nasal passages or across their skin barrier without experiencing adverse symptoms. Pathogenicity begins the moment skin integrity fails. A razor nick, a mat burn from jiu-jitsu, or a picked cuticle can transform benign surface flora into a destructive infection. By learning to distinguish innocuous scrapes from aggressive bacterial colonization, you can intervene before systemic complications emerge.
📌 Key Takeaways:
- Initial Presentation: Early staph rarely resembles an open ulcer; it begins as minor folliculitis, small pus-filled sores, or an inflamed bump easily mistaken for a spider bite.
- Tactile Markers: Rapidly escalating skin warmth and tenderness, accompanied by a firm, indurated center, indicate active bacterial proliferation beneath the epidermis.
- Clinical Escalation: Rapidly spreading redness traveling outward from a central lesion signals cellulitis symptoms or MRSA, requiring an immediate bacterial skin culture and targeted antibiotic treatment.
The Subtle Shift From Minor Irritation to Staph Colonization
The boundary between routine dermatological friction and an active staph outbreak is surprisingly narrow. Human skin acts as a dynamic shield, housing millions of microscopic organisms. Staphylococcus aureus is an opportunistic colonizer. It rests harmlessly on stratum corneum cells until a physical disruption exposes the warm, nutrient-rich dermis underneath.
Initial colonization often masquerades as benign folliculitis. You might notice clusters of small, pinprick-sized bumps around hair follicles on your thighs, neck, or underarms. Unlike standard sweat pimples caused by trapped sebum, staph-driven folliculitis carries a sharp, stinging pain when touched. The surrounding tissue swells slightly, presenting a flushed, rose-colored ring. Friction from tight synthetic clothing accelerates this entry phase by driving surface bacteria into newly irritated pores. If the immune system fails to contain the microbes at the follicular level, the bacteria release toxins that liquefy adjacent cells, converting a surface annoyance into an invasive problem.
Reading the Physical Clues: Boils, Pustules, and Honey Crusts
Staph exhibits distinct visual signatures depending on how deep the bacteria penetrate and which specific toxins they produce. Recognizing these specific signatures removes dangerous guesswork.
When staph penetrates deep into the hair follicle and surrounding subcutaneous tissue, it manifests as boils and furuncles. These begin as firm, tender nodules beneath the skin surface, often measuring between 0.5 and 2 centimeters during the first 36 hours. Over two to three days, the center softens as cellular debris and white blood cells form a visible head of pus. When multiple furuncles cluster together beneath deeper tissue planes, they form a carbuncle, a severe, highly contagious mass that frequently triggers chills and low-grade systemic fevers.
Superficial infections present a completely different visual pattern. Pediatric and athletic populations frequently encounter impetigo, a highly contagious skin infection thoroughly documented by institutions like the Cleveland Clinic. Early-stage impetigo starts as fragile micro-vesicles or blisters that rupture under minimal friction. The hallmark indicator is impetigo crusting: raw, weeping lesions that dry into distinctive, sticky, honey-colored crusts.
Patient discussions across athletic forums and clinical networks routinely show that individuals dismiss these early crusts as simple eczema flares or persistent cold sores. Delaying care allows the bacteria to spread through direct touch across families and sports teams.
| Infection Type | Early Visual Marker | Tissue Depth | Immediate Primary Risk |
|---|---|---|---|
| Folliculitis | Clustered, red, pinpoint bumps around hair follicles | Superficial epidermis | Progression into deeper furuncles |
| Furuncle (Boil) | Hard, painful nodule developing a central white or yellow pus cap | Dermis and subcutaneous layer | Carbuncle formation; scarring |
| Impetigo | Fluid-filled vesicles weeping into honey-colored crusts | Outer stratum corneum | Rapid household transmission |
| Cellulitis | Expanding, diffuse, boundary-free erythema with taut skin | Deep dermis and subcutaneous fat | Sepsis and lymphatic invasion |
When Redness Spreads: Tracking Cellulitis and MRSA
The most dangerous phase of an untreated staph infection occurs when localized bacteria breach cellular defenses and migrate into adjacent dermal architecture. This transition marks the onset of cellulitis symptoms.
Cellulitis does not produce a neat, contained pimple. Instead, it creates spreading redness that radiates across the limb or face with remarkable speed. The skin takes on a tight, glossy appearance, frequently developing a pitted texture reminiscent of an orange peel (known clinically as peau d'orange). Skin warmth and tenderness become impossible to ignore. Laying the back of your hand against the affected patch reveals a distinct heat radiant enough to feel through clothing.
Emergency physicians routinely rely on a straightforward clinical marker: drawing a clean ink line along the perimeter of the red patch. If the inflammation surges beyond that boundary over four to six hours, rapid tissue invasion is underway.
The emergence of methicillin-resistant Staphylococcus aureus (MRSA skin infection) complicates this picture. MRSA has bypassed clinical settings and established deep roots within community environments, including commercial gyms, dormitories, and daycares. An early MRSA lesion typically resembles a raised, purple-red bump crowned by a dark or necrotic center. Patients almost uniformly report: "I woke up with a bad spider bite." True spider bites are rare; an unexplained, rapidly swelling necrotic bump is statistically far more likely to be an aggressive MRSA presentation requiring urgent clinical evaluation.
Diagnostic Realities: Bacterial Cultures and Targeted Medical Care
Visual inspection offers essential clues, but empirical observation cannot identify antibiotic resistance profiles. Relying entirely on visual guesswork leads to treatment failure when confronting resistant pathogens.
A clinician managing a suspicious, weeping lesion will perform a bacterial skin culture. The physician swabs drainage from active pus-filled sores or takes a needle aspirate from an intact pustule. The laboratory plates the sample, isolates the bacterial colony within 24 to 48 hours, and runs antibiotic susceptibility panels. This laboratory diagnostic test prevents patients from wasting precious time on ineffective first-generation penicillins when dealing with a resistant pathogen.
Empiric antibiotic treatment must begin immediately if red streaks radiate toward lymph nodes or if a systemic fever exceeds 100.4°F (38°C). For mild, non-resistant surface infections, clinicians prescribe topical mupirocin ointment alongside antiseptic chlorhexidine washes. Deep abscesses require professional incision and drainage (I&D). Attempting to squeeze, pop, or lance an early staph nodule at home is dangerous. Self-draining forces viable bacteria deeper into vascular beds, dramatically increasing the risk of bloodstream infections or necrotizing soft-tissue damage.
Household Containment and Stopping Community Transmission
Staph survives on non-porous surfaces, such as weight-lifting equipment, wrestling mats, shared razors, and towels, for days. Stopping community spread requires strict physical barriers and hygiene discipline.
Cover every draining sore with sterile, non-stick dressings secured by water-resistant tape. Keep open wounds entirely sealed until the skin completely heals over. Wash workout clothes and bed linens in hot water cycles exceeding 130°F (54°C), followed by high-heat tumble drying. Household members should never share personal grooming instruments, including nail clippers, washcloths, or bar soap. For individuals experiencing recurrent, stubborn bouts of boils, physicians often recommend a nasal decolonization protocol using prescription antibiotic ointment alongside regulated bleach baths to lower baseline bacterial load across the body.
Frequently Asked Questions (FAQ)
Q1: How can I distinguish between an early staph infection and a routine spider bite?
A1: True spider bites usually present two distinct puncture marks accompanied by immediate, localized stinging. Early staph, particularly a community-acquired MRSA bump, starts as a tender nodule that swells rapidly, accumulates pus, and radiates noticeable heat without any history of direct insect contact.
Q2: Will early-stage staph heal on its own without prescription intervention?
A2: Mild superficial folliculitis occasionally clears with warm compresses and antimicrobial washes. Once staph forms deep boils, displays honey-colored impetigo crusting, or shows expanding borders, prescription topical or oral antibiotics are necessary to halt progression.
Q3: What visual sign indicates that a staph infection is becoming an emergency?
A3: Red streaks moving upward from the lesion toward the heart (lymphangitis), swelling that spreads beyond a marked pen line within hours, a high fever, confusion, or a rapidly darkening, purple-black core are red-flag indicators demanding emergency room care.
Halting Tissue Invasion Before Permanent Harm
Early staph infections present a narrow diagnostic window where treatment remains straightforward, fast, and non-invasive. The primary danger lies in human complacency, interpreting a hot, pulsating red welt as a routine pimple or an insect bite.
Pay close attention to what your skin communicates. Watch for unusual warmth, note the speed of outward swelling, and look for classic markers like honey-colored crusts and deep, unyielding nodules. If a skin blemish behaves aggressively within a twelve-hour window, seek a formal medical evaluation. Prompt culturing and targeted medical treatment ensure a minor bacterial exposure resolves safely without escalating into a destructive deep-tissue emergency.
