Why Everyone Is Searching Cephalexin: Critical Mistakes Most Patients Make
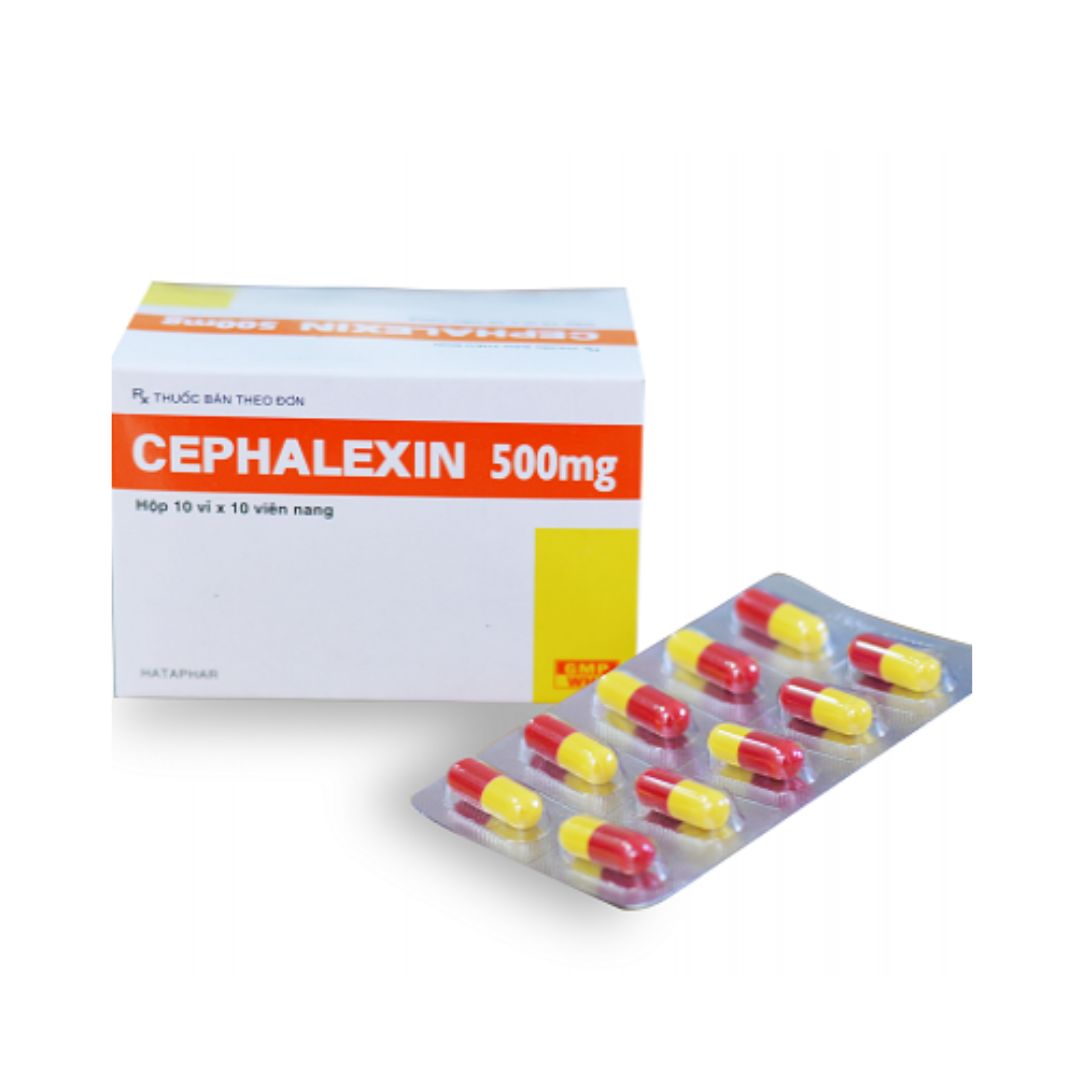
Every day, tens of thousands of patients type "cephalexin para que sirve" into search engines after leaving urgent care clinics with a white-and-green capsule bottle. The query, Spanish for "what is cephalexin used for", has quietly climbed global and domestic medical search indexes as bilingual households, telehealth platforms, and cross-border pharmacy traffic surge. Despite its ubiquity, confusion about this half-century-old drug remains remarkably high.
Cephalexin, sold for decades under the brand name Keflex, is a workhorse oral antibiotic designed to eliminate specific bacterial infections. Yet clinical audits show that up to 30% of outpatient antibiotic prescriptions are mismatched or unnecessary. When taken for viral head colds or abandoned halfway through a cycle, this dependable medication quickly transforms from a cure into a catalyst for complications.
📌 Key Takeaways:
- Targeted Action: Cephalexin is a first-generation cephalosporin that destroys bacteria by dismantling cell walls; it has zero efficacy against viral colds, influenza, or COVID-19.
- Primary Prescriptions: Doctors routinely issue it for uncomplicated urinary tract infections, strep throat, and skin and soft tissue infections caused by Staphylococcus aureus and streptococcal strains.
- Safety Guardrails: While the historical fear of a 10% cross-allergy with penicillin has dropped to roughly 1% to 2% in modern clinical evaluations, patients with past anaphylactic shocks must avoid it.
The Bilingual Search Surge Behind a Decades-Old Antibiotic
Search engines reflect the raw realities of healthcare literacy. The persistent popularity of the phrase "cephalexin para que sirve" in English-speaking markets highlights a structural disconnect: patients receive their prescription bags with printed monographs, yet walk out unsure of what the medication actually targets. Telehealth consultations, which often last under seven minutes, routinely miss deeper counseling discussions regarding proper intake.
First synthesized in 1967, cephalexin became a staple of modern medical care under the Keflex generic name. It belongs to the first-generation cephalosporin family. Its primary function is bactericidal, meaning it kills bacteria rather than merely slowing down reproduction. It does this by binding to penicillin-binding proteins, preventing microbes from constructing peptidoglycan walls. Under internal osmotic pressure, the invading bacteria burst and perish.
Because the drug costs as little as $10 to $25 out of pocket for a standard course, clinicians rely on it as a frontline defender. But low cost breeds casual use. When families keep leftover capsules in medicine cabinets, self-medication attempts skyrocket whenever someone develops an undiagnosed throat scratch or toothache.
What Cephalexin Actually Treats, and What It Fails to Touch
Cephalexin excels against gram-positive organisms. In routine practice, it targets superficial and moderately deep skin and soft tissue infections like cellulitis, impetigo, and infected abrasions dominated by Staphylococcus aureus. For patients unable to take amoxicillin due to non-severe rashes, doctors often choose cephalexin as an effective alternative for strep throat treatment.
Another major therapeutic territory is the uncomplicated urinary tract infection (UTI), typically caused by susceptible strains of Escherichia coli or Proteus mirabilis. It also sees widespread off-label and on-label use for mild bone infections and dental abscesses.
Where does it fail? Cephalexin is useless against viral illnesses. It cannot treat influenza, bronchitis, sinus congestion caused by seasonal allergies, or ordinary sore throats linked to rhinoviruses. Prescribing or swallowing it for a systemic viral cough provides zero relief while actively exposing gut flora to collateral destruction.
Furthermore, standard cephalexin possesses zero activity against Methicillin-resistant Staphylococcus aureus (MRSA). When clinicians misdiagnose a community-acquired MRSA boil as standard staph and write an order for cephalexin, the infection can escalate into severe, deep-tissue abscesses within 48 to 72 hours.
Dosing Realities and Clinical Benchmarks
Safe administration hinges on maintaining therapeutic blood concentrations around the clock. Because cephalexin has a short serum half-life of roughly one hour, oral antibiotic administration requires strict dosing intervals, usually every 6 or 12 hours depending on the pathogen.
| Infection Type | Standard Adult Regimen | Typical Causative Pathogens | Clinical Watchpoint |
|---|---|---|---|
| Skin & Soft Tissue (Cellulitis, Folliculitis) | 500mg every 12 hours (or 250mg every 6 hours) for 5, 7 days | Staphylococcus aureus, Streptococcus pyogenes | Ineffective against MRSA; monitor for expanding margins. |
| Uncomplicated Urinary Tract Infection (UTI) | 500mg every 12 hours for 7, 14 days | Escherichia coli, Klebsiella pneumoniae | Urine culture required; high regional E. coli resistance rates. |
| Streptococcal Pharyngitis (Strep Throat) | 500mg every 12 hours for 10 days | Group A Streptococcus | Must complete full 10-day cycle to prevent acute rheumatic fever. |
| Bone & Joint Infections (Osteomyelitis) | 1,000mg to 1,500mg divided every 6 hours for 4, 6 weeks | Susceptible staphylococcal strains | Requires renal function monitoring; higher gastrointestinal distress rates. |
For an adult suffering from an acute cutaneous issue, a dosage of 500mg taken twice daily is the baseline prescription. Severe cases can warrant up to 4,000mg per day split into four distinct doses. Skipping doses or extending the hours between intake causes drug concentrations in the blood to dip beneath the minimum inhibitory concentration, giving bacteria an immediate window to recuperate.

The Penicillin Allergy Conundrum and Real Cross-Reactivity Hazards
Generations of medical textbooks warned that up to 10% of penicillin-allergic patients would suffer an allergic reaction if exposed to cephalosporins. That warning has been revised. Modern pharmacological research confirms that early cross-reactivity studies in the 1970s suffered from chemical contamination: early cephalosporin batches were manufactured with traces of penicillin itself.
Contemporary immunologic reviews demonstrate that penicillin allergy cross-reactivity with cephalexin hovers between 1% and 2%. The actual risk depends on structural similarities within the drug's R1 chemical side chain. Cephalexin shares an identical side chain with ampicillin, which increases the likelihood of a shared immune response compared to later-generation cephalosporins like ceftriaxone.
Risk stratification is essential. A patient who experienced a mild childhood rash from penicillin can often take cephalexin safely under clinical observation. Conversely, individuals with a confirmed history of severe Type-I IgE-mediated reactions, such as anaphylaxis, throat swelling, bronchospasm, or toxic epidermal necrolysis, must avoid cephalexin entirely. The immune response in those rare crossovers can be catastrophic.
Why Stopping Early Escalates Antibiotic Resistance Risks
Feeling healthy on day three of a seven-day antibiotic course is a trap. When treatment starts, cephalexin quickly eradicates the weakest bacterial populations. The patient's fever breaks, swelling subsides, and energy returns. But the most resilient bacterial variants survive deep within tissue beds.
Ignoring course completion guidelines allows these hardy survivors to rebound. Unchallenged by adequate antibiotic levels, they exchange genetic material through horizontal gene transfer, selecting for thicker cell walls or producing beta-lactamase enzymes. This sequence accelerates wider antibiotic resistance risks across communities, turning common infections into untreatable clinical crises.
Premature cessation also does nothing to prevent common side effects. Nausea, mild abdominal cramping, and loose stools affect roughly 5% to 8% of patients taking cephalexin. Most digestive symptoms are manageable by taking capsules with food or a glass of water. However, unprovoked watery diarrhea lasting multiple days demands immediate lab work: cephalexin can strip protective gut bacteria, permitting Clostridioides difficile to flourish and trigger life-threatening colitis.
Frequently Asked Questions (FAQ)
Q1: Can I drink alcohol while taking a 500mg cephalexin prescription?
A1: Cephalexin does not produce a violent disulfiram-like reaction with alcohol the way metronidazole does. However, alcohol irritates the stomach lining, exacerbates dizziness, and impairs the immune system's recovery timeline. Medical professionals advise avoiding alcohol until the full prescription is complete.
Q2: What happens if I accidentally miss a scheduled dose?
A2: Take the missed capsule as soon as you remember. If it is already close to the time of your next scheduled dose, skip the forgotten capsule and resume your standard timetable. Never take two 500mg capsules at the exact same moment to compensate, as this spikes gastrointestinal toxicity without improving bacterial clearance.
Q3: Is cephalexin safe during pregnancy and breastfeeding?
A3: Cephalexin carries an established safety track record in obstetrics. The FDA categorizes it as a drug that crosses the placenta without demonstrating documented risks of fetal malformations in controlled human studies. Trace amounts enter breast milk, which may rarely cause transient loose stools in nursing infants, but pediatricians routinely clear it for postpartum maternal infections.
Responsible Antibiotic Stewardship
Cephalexin remains one of modern medicine's most reliable defenses, curing millions of bacterial illnesses every year without hospital intervention. Its value depends entirely on how prudently patients and clinicians deploy it. In an environment saturated with fragmented medical advice, self-treating an ambiguous infection with leftover pills from an old bottle invites treatment failure and dangerous complications.
When prescribed this medication, confirm the exact bacterial target with your provider, commit to the prescribed schedule down to the hour, and finish every dose. Protecting the therapeutic power of basic antibiotics is a clinical responsibility shared by every household.
