Visual Progression Guide: Identifying Brown Recluse Spider Bite Stages Through Real Lesions
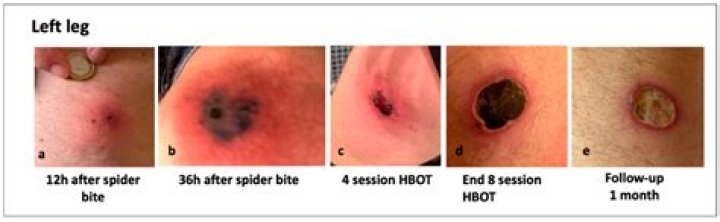
Emergency rooms across the southern and central United States encounter hundreds of self-diagnosed spider bites every week. Most patients arrive convinced that a small, violin-marked arachnid ambushed them while they slept. Yet retrospective clinical reviews consistently show that over **80%** of these self-reported wounds are not arachnid encounters at all, but rather stubborn staph infections, fungal blooms, or contact dermatitis. Identifying genuine dermal damage requires understanding the specific biological footprint left by Loxosceles reclusa.
When an actual bite occurs, the venom operates through a rigid cellular schedule. Documented updates outlined in a detailed Prevention Report and poison control registries across the Midwest clarify that confirmed envenomations unfold over distinct, highly visible intervals. Telling a benign welt apart from an escalating necrotic lesion protects patients from both unnecessary panic and dangerous clinical delays.
📌 Key Takeaways:
- Initial Presentation: Genuine bites are rarely agonizing on contact; mild stinging transforms into a tender, violaceous center surrounded by an ischemic ring within **2 to 8 hours**.
- The Necrotic Pivot: Less than **10% to 15%** of verified bites produce extensive tissue necrosis, which solidifies into a dry, sunken black eschar between days 3 and 7.
- Clinical Management: Early surgical incision frequently worsens scarring; supportive wound hygiene, cold packs, and delayed wound debridement remain the gold-standard protocol.
How Spider Venom Toxicity Triggers Dermal Breakdown
The brown recluse does not possess powerful fangs. Its mouthparts are tiny, rarely piercing clothing or thick calluses. When the spider feels crushed against human skin inside a bedsheet or work boot, it deploys a microscopic payload containing sphingomyelinase D. This specific enzyme serves as the primary engine of spider venom toxicity, cleaving cell membranes and setting off a chaotic inflammatory chain reaction.
Sphingomyelinase D targets endothelial cells lining microscopic blood vessels beneath the skin. The enzyme strips away cell surface markers, signaling circulating neutrophils to gather at the site. These white blood cells release destructive enzymes, clogging local microcirculation. Without blood flow, surrounding capillaries collapse. The skin essentially suffocates from within.
This localized vascular thrombosis explains why early brown recluse wounds behave differently than wasp stings or mosquito bites. There is no rapid surge of histamine-driven swelling that peaks in twenty minutes. Instead, the tissue quietly starves, triggering localized dermal necrosis that becomes increasingly obvious as the cellular scaffold disintegrates over several days.
Hours 2 to 24: Spotting Bullseye Erythema and the Central Blister
The initial bite usually goes unnoticed. Victims often wake up thinking they brushed against a briar or sustained a minor mosquito nip. True progression begins between 2 and 8 hours post-contact, as localized pain transitions from a faint ache to a persistent, throbbing burn.
The visual marker during this first full day is the classic red, white, and blue pattern. A peripheral ring of erythema outlines the site. Directly inside this red margin sits a pale, blanched halo of vasospasm where microvessels have clamped shut. At the absolute center, the skin turns a faint bluish-gray or deep violet. This dynamic bullseye erythema is distinctive because the center sinks rather than rises.
By hour **12 to 24**, fluid builds beneath the dead epidermal layer, generating a tense central blister. Unlike fluid-filled blisters from burns, this lesion often contains dark, hemorrhagic serum. The surrounding skin feels firm and warm to the touch, yet the blanched zone directly under the blister may lose sensation as superficial nerve endings shut down from microvascular ischemia.
Clinical Milestones Across the Cutaneous Timeline
Medical teams monitor suspected envenomations by tracking visual milestones across the skin surface. The vast majority of wounds resolve spontaneously without severe ulceration, but patients experiencing deeper envenomation follow a recognizable pathophysiological sequence.
| Phase & Timeline | Visual Presentation | Pathological Activity | Recommended Clinical Care |
|---|---|---|---|
| Phase 1: Hours 0, 8 | Faint punctum, mild redness, central pallor | Sphingomyelinase D initiates capillary thrombosis | Ice packs, elevation, baseline observation |
| Phase 2: Hours 8, 48 | Hemorrhagic central blister, ischemic halo | Neutrophil infiltration, local dermal ischemia | Rest, oral pain relievers, avoid heat application |
| Phase 3: Days 3, 7 | Sunken, violaceous skin hardening into a dark plaque | Full-thickness skin death, dry gangrenous transformation | Wound cleaning, monitor for secondary infection |
| Phase 4: Weeks 2, 8 | Open cratered ulcer with peripheral granulation tissue | Eschar sloughing, slow wound contraction | Delayed debridement, topical barriers, grafting if large |
Days 3 to 7: Eschar Formation and Spreading Dermal Necrosis
As the initial blister ruptures between the third and fifth days, the underlying tissue dries and darkens. What was once soft skin collapses into a depressed, leather-like plate. This phase marks true eschar formation. Unlike common scabs made of coagulated blood, this eschar consists of full-thickness dead skin held together by dense fibrin.
The margins during this period provide critical diagnostic insight. In non-necrotic staph infections, lesions expand symmetrically outward in a swollen dome. Recluse necrosis behaves differently: it sinks inward, showing asymmetrical margins that track along gravitational lines or local blood supply vectors. The surrounding ring turns from fiery red to a dull mahogany.
Patients experience varying degrees of discomfort at this stage. Some report sharp, lancinating pain whenever tension stretches the hardening plaque, while others feel almost numb across the dark center because superficial dermal receptors have broken down. The true danger here is opportunistic pathogens. When the skin barrier fails, a secondary bacterial infection like cellulitis or methicillin-resistant Staphylococcus aureus can take root along the necrotic borders.
Weeks 2 to 8: The Ulceration Timeline and Wound Debridement Decisions
The ulceration timeline enters its slowest phase between the second and third weeks. The rigid black eschar begins to separate from healthy tissue around its perimeter. Cracks appear, and the dead cap slowly sloughs off, revealing an open ulcer crater that can measure anywhere from **1 to 5 centimeters** across.
Surgeons in the mid-twentieth century routinely cut out suspected bites within forty-eight hours. Modern toxicology has thoroughly discarded that aggressive practice. Excising tissue before the venom burns itself out simply widens the boundary of necrotic damage, leaving larger scars. Today, clinical teams wait weeks until the margin between dead tissue and viable tissue is distinct before performing targeted wound debridement.
Once clean, the ulcer bed fills slowly with bright pink granulation tissue. Healing relies on natural wound contraction. Superficial bites under **1 centimeter** typically close completely within **4 to 6 weeks**, leaving a pale, slightly depressed scar. Deeper wounds stretching across fatty tissues, such as the thighs or buttocks, may require **8 to 12 weeks** of diligent dressing changes and occasional skin grafting.
Recognizing Systemic Loxoscelism and Emergency Complications
While cutaneous injuries demand careful wound care, the brown recluse venom can occasionally produce a life-threatening whole-body reaction. This complication, known as systemic loxoscelism, occurs in roughly **1% to 2%** of confirmed bites, appearing more frequently in small children and immunocompromised adults.
Systemic symptoms appear rapidly, usually within **24 to 72 hours** of the initial bite, and do not always correlate with the size of the skin lesion. A tiny superficial welt can still unleash enough venom to trigger severe red blood cell destruction. Key warning signs require immediate emergency intervention:
- Spiking fevers accompanied by severe chills, joint pain, and nausea
- A diffuse, sandpapery rash spreading across the torso and limbs
- Dark tea-colored or red urine, signaling intravascular hemolysis
- Sudden jaundice visible in the sclera of the eyes or under the tongue
- Extreme fatigue and confusion caused by rapid hemoglobin breakdown
When massive hemolysis dumps free hemoglobin into the bloodstream, the kidneys face acute strain, risking renal failure. Clinical case studies, including severe presentations of septic limb necrosis documented in Elsevier medical archives, demonstrate that when profound tissue necrosis converges with systemic bacteremia, surgical limb salvage teams must act fast to prevent total sepsis.
The NOT RECLUSE Diagnostic Filter: Weeding Out False Alarms
Medical entomologist Dr. Richard Vetter developed the "NOT RECLUSE" mnemonic to help clinicians and patients rapidly rule out spider bites. Because real brown recluse spiders inhabit a defined geographic range, primarily from eastern Kansas and Texas through Kentucky and Tennessee, bites occurring in the Pacific Northwest, New England, or Canada are extraordinarily improbable.
The criteria highlight visual and contextual red flags that argue against a recluse bite:
- N (Numerous): Recluses rarely bite multiple times in one night. If you count five red bumps, bedbugs or fleas are the likely culprits.
- O (Occurrence): Bites happen indoors during quiet contact. If you received the bite while gardening under direct sunlight, suspect horseflies or wasps.
- T (Timing): Bites spike between April and October; winter bites in cold rooms are uncommon.
- R (Red Center): Real recluse bites show a sinking, pale, or violaceous center. A raised, swollen red bump is typical of an insect sting.
- E (Elevated): Recluse lesions sink downward. A raised, fluctuant dome almost always points to a bacterial abscess.
- C (Chronic): A wound that remains unchanged for four months without forming an eschar is not a spider bite.
- L (Large): Dermal necrosis that balloons beyond 10 centimeters within twenty-four hours points toward necrotizing soft-tissue infection, not arachnid venom.
- U (Ulcerates early): Bites do not turn into open weeping ulcers within 6 hours. Sloughing takes days.
- S (Swollen): Massive limb-wide edema rarely occurs unless secondary cellulitis takes hold.
- E (Exudative): Recluse bites produce minimal dry crusting; lesions draining thick white pus indicate a bacterial infection like MRSA.
Frequently Asked Questions (FAQ)
Q1: How can I tell the difference between a brown recluse bite and an early MRSA infection?
A1: MRSA typically forms a raised, tender, red nodule with a bright yellow or white pustule that feels hot and drains cloudy pus within 24 hours. A brown recluse bite sinks in the center, develops an ischemic, pale halo, and forms a firm, dark violet blister rather than an elevated pimple.
Q2: Should I apply a heating pad to reduce the pain of a suspected bite?
A2: Never apply heat to a brown recluse bite. Heat accelerates the enzymatic activity of sphingomyelinase D, speeding up tissue destruction. Instead, apply a cold pack wrapped in a cloth for 10-minute intervals to slow the venom down and reduce localized swelling.
Q3: How long does it take for a necrotic brown recluse bite to completely heal?
A3: Mild envenomations that stay superficial resolve within 2 to 3 weeks without significant scarring. Moderate to severe bites that develop an eschar and open ulcer take between 6 and 12 weeks to close through second-intention healing.
Managing Suspected Bites with Clinical Clarity
Encountering a mysterious, painful skin lesion triggers natural anxiety. The key to successful recovery lies in careful observation rather than frantic home remedies. Slashing the wound, attempting to squeeze venom from the puncture mark, or slathering the site with caustic home pastes will only accelerate tissue necrosis and drive bacteria deep into the fascia.
If you suspect a bite, cleanse the area with basic soap and water, apply cold compresses, elevate the limb, and outline the boundary of redness with a surgical pen. If the center remains flat or sinks into a dark, dusky violet hue over the subsequent forty-eight hours, seek an evaluation from a physician familiar with local arthropod toxicology. Most wounds heal completely with conservative care, provided they are managed with patience, hygiene, and clinical discipline.


