High-Profile Strabismus Cases Spark Surge in Corrective Eye Procedures
When Prince William and Kate Middleton openly shared Lady Louise Windsor’s early childhood journey with esotropia, and how corrective operations restored her ocular alignment, it triggered an unexpected ripple across adult healthcare. For decades, strabismus carried an unspoken, misinformed stigma: patients assumed that if crossed eyes were not repaired in infancy, the window closed permanently. That myth is crumbling. Specialist ophthalmic centers report an unprecedented influx of mature patients seeking corrective operations, driven by candid public disclosures, modern surgical innovations, and broader healthcare access.
The operational shift is visible across academic medical centers nationwide. As detailed in a Stanford Medicine report on adult eye misalignment, specialized tertiary services are redesigning intake pathways to accommodate mature individuals who spent years assuming their ocular deviation was purely cosmetic and untreatable. Today, clinical outcomes prove that realigning ocular tissue delivers profound functional restoration, rescuing patients from debilitating double vision, spatial confusion, and social isolation.
📌 Key Takeaways:
- The Clinical Shift: Adult strabismus surgery is no longer classified as cosmetic; it is an essential reconstructive procedure that restores binocular fusion and depth perception.
- Modern Innovation: The adoption of adjustable sutures allows surgeons to fine-tune extraocular tension post-operatively while the patient is awake, pushing success rates beyond 80%.
- Systemic Impact: High-profile royal and celebrity discussions have dismantled decades of stigma, driving record adult consultations across North American eye clinics.
How Public Spotlights Broke Decades of Medical Hesitation
For generations, the cultural narrative around strabismus remained locked in elementary school classrooms. Children wore adhesive patches over dominant eyes, underwent corrective procedures before age seven, or wore thick refractive lenses. When adults presented with inward-turning eyes (esotropia) or outward-drifting eyes (exotropia), general practitioners frequently told them nothing could be done safely. The brain, conventional wisdom claimed, could no longer adapt to straight visual axes.
That defeatist medical stance fostered private suffering. Adults developed subtle coping mechanisms: tilting heads during client presentations, avoiding direct eye contact on video calls, or turning off desk monitors to manage visual strain. Public disclosures changed the conversation. When Lady Louise Windsor's ocular history entered international headlines following her high-profile public appearances, patient communities noticed. Online support forums, including Reddit’s r/Strabismus, logged spikes in queries from professionals aged 25 to 65 questioning why they were abandoned to live with crossed visual axes.
Cultural transparency dissolved the shame. Patients discovered that thousands of adults share their visual disorientation. The realization that surgical intervention could untangle double vision (diplopia) and eliminate cervical pain caused by persistent head turns drove consultations upward across ophthalmic institutions throughout 2024, 2026.
The Functional Reality Behind Adult Eye Misalignment
Crossed eyes in adults stem from distinct biological pathways compared to congenital pediatric cases. While children frequently develop misalignment from refractive imbalance or neurological developmental pauses, adult onset often follows distinct trauma, microvascular cranial nerve palsies, thyroid eye disease, or decompensating childhood strabismus that the brain can no longer muscle through.
The daily toll is physical. When visual axes diverge, the visual cortex receives conflicting images. Children suppress the aberrant image, risking permanent amblyopia (lazy eye). The mature brain cannot suppress signals as easily. The result is chronic, disorienting diplopia. Sufferers misjudge stairs, struggle to drive at highway speeds, and endure splitting tension headaches from subconciously squinting one eye shut.
Corrective intervention is restorative, functional surgery. By realigning the visual lines, surgeons resolve visual confusion and expand peripheral visual fields. The historical excuse used by commercial insurers, labeling the surgery "purely cosmetic", has collapsed under clinical evidence documenting gains in binocular vision restoration and psychological stability.
Surgical Mechanics: Repositioning the Extraocular Muscles
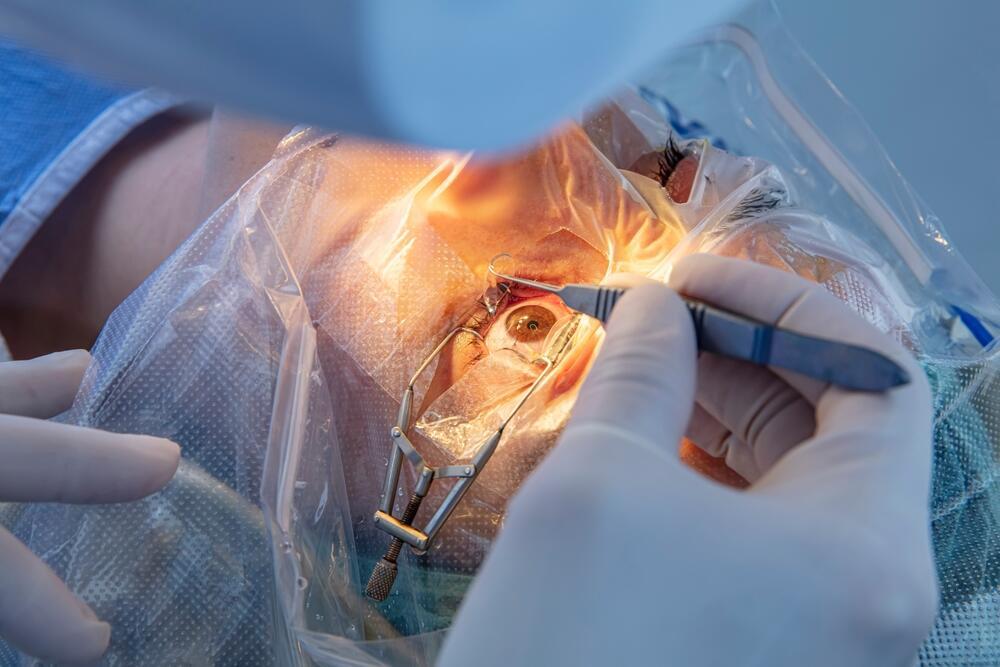
The procedure does not involve cutting into the globe of the eye, lasers, or corneal shaving. Instead, the ophthalmic surgeon works entirely on the external surface beneath the clear conjunctival membrane, manipulating the six delicate extraocular muscles that orchestrate eyeball trajectory.
During the operation, the surgeon accesses the targeted muscle through a microscopic incision. If a muscle pulls too tightly, pulling the eye inward, the surgeon performs a recession, detaching the muscle from its anatomical insertion point and stitching it further back along the sclera to slacken tension. Conversely, if a muscle is lax, a resection or plication shortens the tissue, pulling the eye straight. Precision matters down to fractions of a millimeter: a 1-millimeter variance can alter eye alignment by two to three degrees.
| Surgical Factor | Pediatric Strabismus Protocol | Adult Strabismus Protocol |
|---|---|---|
| Primary Objective | Prevent amblyopia; establish baseline neural binocular pathways. | Eliminate diplopia; recover binocular fusion; expand field of view. |
| Anesthesia Approach | Full general anesthesia exclusively. | General or monitored conscious sedation with local retrobulbar blocks. |
| Suture Technique | Standard absorbable sutures tied permanently during surgery. | Adjustable suture loops fine-tuned post-operatively while awake. |
| Primary Success Rate | 70%, 80% single-operation alignment. | 80%, 88% target alignment using adjustable techniques. |
The introduction of adjustable sutures revolutionized adult outcomes. Instead of permanently securing the muscle while the patient is unconscious, the surgeon secures the repositioned muscle with a slipknot. Hours later, or the following morning, the surgeon assesses the patient’s conscious eye alignment. Using topical numbing drops, the surgeon nudges the suture millimeters forward or backward until the patient confirms that double vision has vanished. This real-time calibration significantly cuts the need for secondary re-operations.
Recovery Realities and Managing Post-Operative Expectations
The physical strabismus surgery recovery time is surprisingly brief, though visually jarring in its early stages. Patients leave the surgical center the same day. The eye appears bright red, resembling an aggressive subconjunctival hemorrhage; this pooling of surface blood is harmless and clears across two to four weeks. Discomfort feels like an eyelash caught under the lid rather than sharp ocular pain.
Most patients return to desk work and screen tasks within three to seven days, avoiding heavy lifting, swimming, and eye makeup for two weeks. However, the neural adaptation period takes longer. The brain must rewire how it processes newly aligned inputs.
During the first fortnight, mild, transient ghosting or prism-like shifts can occur as visual cortices adjust. For over 80% of patients, this settles into stable, single binocular vision within six weeks, eliminating the chronic neck strain that plagued their pre-operative lives.
Who Benefits Most Versus Who Faces Elevated Risks
Not every misalignment case is an open-and-shut surgical victory. Careful preoperative workups separate candidates who will gain life-changing fusion from those who risk complications.
Ideal Candidates:
- Adults with constant or intermittent double vision from decompensated strabismus, nerve injury, or past trauma.
- Patients suffering visual confusion or physical neck spasms from head tilts used to keep vision single.
- Individuals with stable deviation measurements over a baseline tracking period of three to six months.
Cases Requiring Extreme Caution:
- Patients with intractable sensory anomalies, where previous childhood surgeries caused abnormal retinal correspondence. In these rare cases, physically straightening the eyes can induce persistent double vision the brain cannot suppress.
- Uncontrolled thyroid eye disease. Active orbital inflammation must completely burn out before touching muscle tissue.
- Patients with unrealistic expectations of rapid, perfect symmetry down to microscopic fractions. Eye alignment is biological, not mechanical, and minor residual drift can occur over decades.
Frequently Asked Questions
How painful is the recovery process after adult cross eye surgery?
Pain levels are moderate. Most patients manage initial soreness with over-the-counter acetaminophen or ibuprofen. The eye feels scratchy, dry, and irritated for 48 to 72 hours due to surface sutures, but severe deep-socket pain is uncommon.
Does adult insurance cover strabismus surgery, or is it billed as cosmetic?
Most major commercial insurers and Medicare cover the operation as medically necessary reconstructive surgery. Coverage typically requires documenting double vision, abnormal head posture, or visual field restriction.
Can crossed eyes recur years after a successful operation?
Yes. Muscles are living, dynamic tissues. While primary operations succeed in roughly 80% to 88% of cases, natural aging, tissue laxity, or underlying neurological drift can cause gradual slippage decades later. Secondary adjustments or prism glasses can manage late recurrences.
The Evolving Path for Adult Vision Care
The surge in adult eye realignments represents a overdue correction in medical culture. Decades of dismissive advice kept millions of adults trapped behind unnecessary physical pain and social anxiety. Today's combination of microsurgical adjustable sutures, precise neuro-ophthalmic mapping, and outspoken cultural role models has brought strabismus out of the shadows. For adults still turning their heads to see a single world, modern surgery offers an open door to clear, aligned, depth-restored vision.