How to Administer Wegovy at Home: The Complete Step-by-Step Injection Site Guide
Administering a weekly dose of semaglutide sounds straightforward until you stand in front of the bathroom mirror with a loaded autoinjector, wondering whether a pinch of lower belly fat will trigger three days of intense nausea. For millions of patients managing chronic weight management and cardiovascular risk, pinpointing the proper tissue layer makes the difference between consistent adherence and debilitating gastrointestinal distress. The delivery landscape expanded further as Novo Nordisk responded to persistent manufacturing bottlenecks; according to a polskieradio.pl Report, the pharmaceutical manufacturer initiated direct sales of Wegovy in multidose and single-dose vials in select markets to supplement its standard pre-filled hardware.
Whether you rely on conventional glass vials with insulin syringes or the ubiquitous auto-reset spring pens, proper technique remains mandatory. Choosing the right spot dictates how smoothly the peptide absorbs into your systemic circulation. Small errors in depth, angle, or regional choice create immediate consequences: localized swelling, painful bruising, or unexpected waves of emesis that derail your routine.
📌 Key Takeaways:
- Approved Anatomical Sites: The abdomen, front of the thigh, and back of the upper arm are the only three clinically cleared zones for subcutaneous semaglutide delivery.
- GI Side Effect Management: Switching from the abdomen to the outer thigh provides noticeable nausea reduction for a substantial subset of patients due to subtle shifts in systemic uptake rates.
- Strict Site Rotation: Injecting into the exact same two-inch radius risks lipohypertrophy, erratic drug absorption, and persistent skin induration.
- Expanding Options: Patients wrestling with needle fatigue now weigh weekly subcutaneous autoinjectors against newly distributed Wegovy vials and emerging daily oral semaglutide alternatives.
The Three Clinically Approved Injection Zones
Subcutaneous injection demands delivery directly into the fatty layer resting between skin and underlying skeletal muscle. If you inject too shallowly, the medication pools intradermally, triggering acute pruritus and hive-like wheals. If you drive the needle too deep into muscle vascularity, the peptide enters systemic circulation too quickly, amplifying acute systemic side effects.
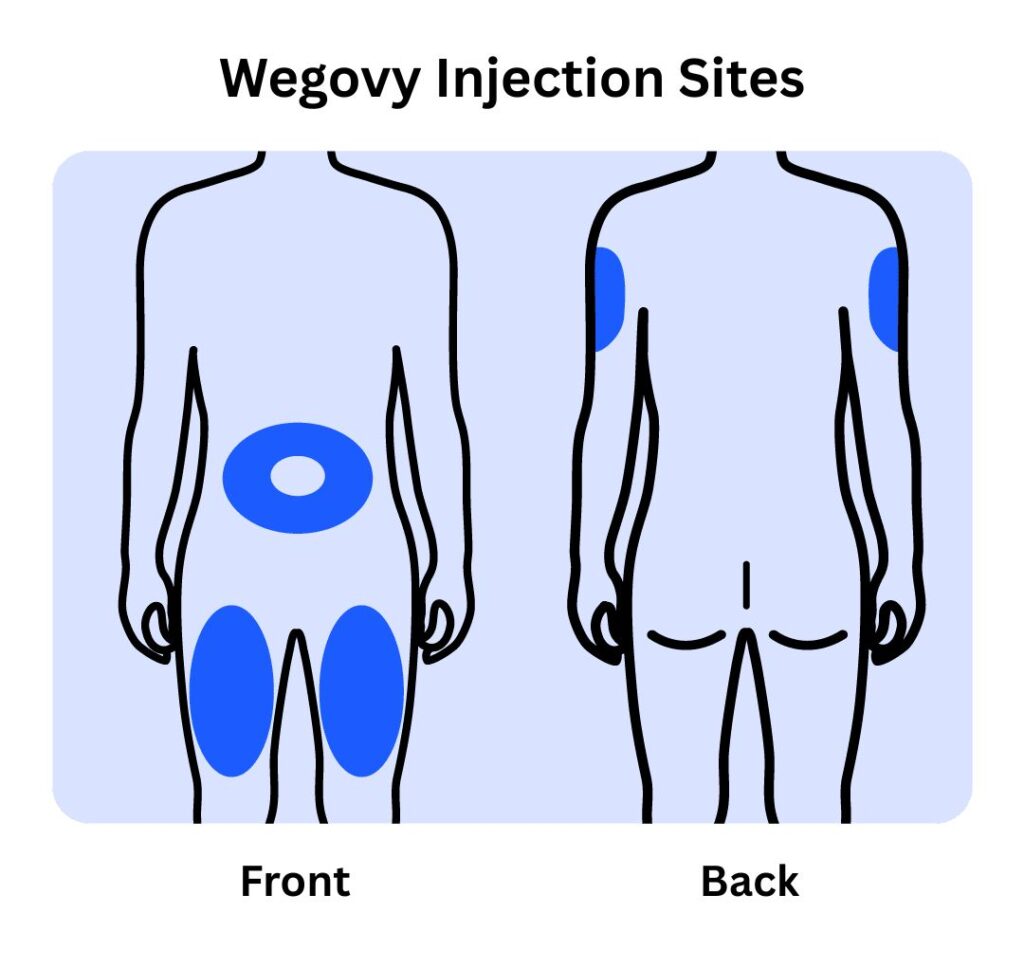
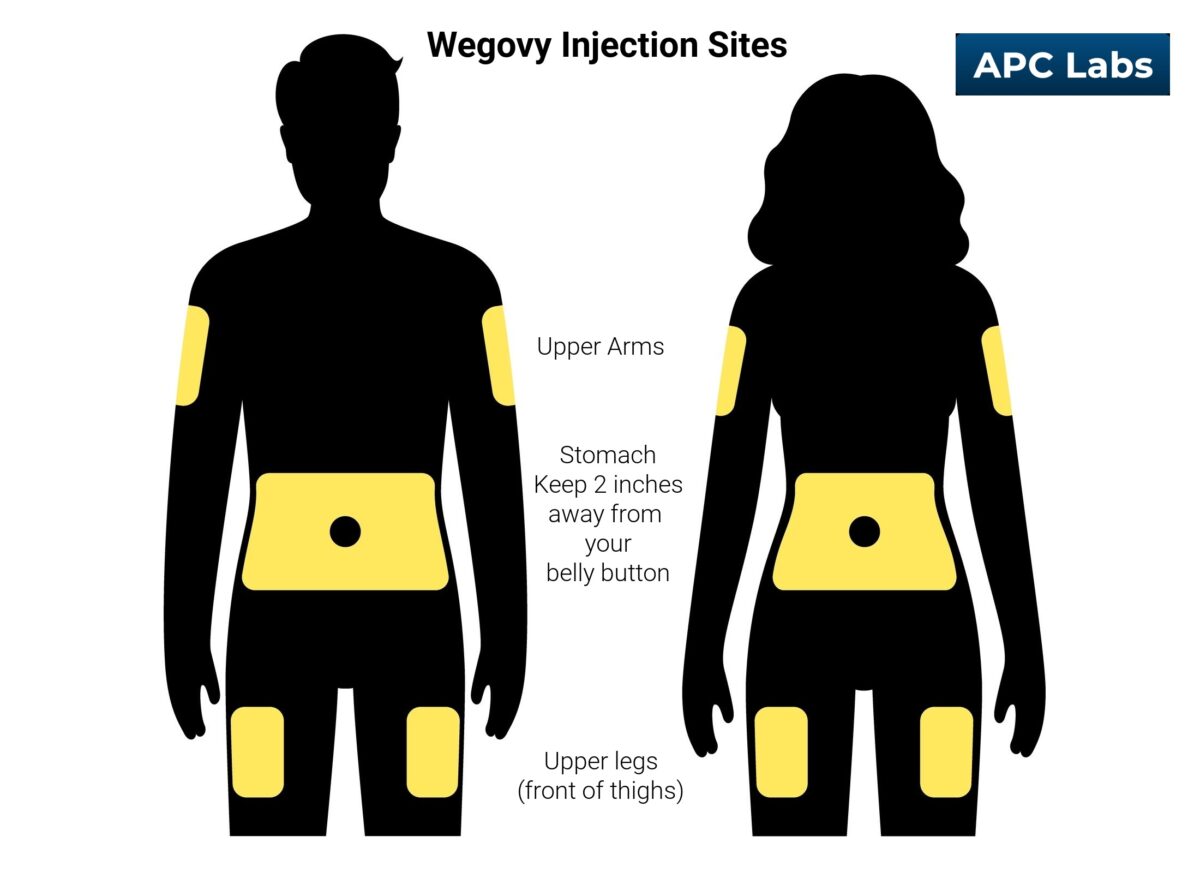
Three specific anatomical zones offer the requisite depth of adipose tissue while minimizing contact with major nerves and blood vessels:
The abdomen injection area represents the most common starting point. Patients utilize the expansive fatty tissue to the left or right of the navel, maintaining at least a strict two-inch perimeter away from the belly button itself. The abdomen provides generous surface area, making self-visualization easy without contorting the torso.
The outer thigh injection site spans the anterior and lateral aspects of the upper leg, roughly midway between the groin and the knee. This zone consists of denser subcutaneous tissue overlying the quadriceps. Many clinicians direct patients here first if abdominal bloating or nausea becomes intolerable.
The upper arm administration site occupies the posterior tricep area, halfway between the shoulder joint and the elbow. While physiologically effective, this location requires either assistance from a caregiver or deliberate contortion against a flat surface to expose the fatty pocket, making it the least popular choice for solo administration.
Pharmacokinetics and the Thigh vs. Abdomen Dilemma
Does your chosen anatomical site alter semaglutide absorption? Officially, drug labeling notes bioequivalence across all three sites. Pharmacokinetic data demonstrates that maximum concentration ($C_{max}$) and total systemic exposure ($AUC$) remain broadly comparable over a steady-state 7-day dosing interval.
Real-world clinical reports and patient registries tell a more nuanced story. Systemic vascular perfusion differs between the mesenteric-adjacent abdominal wall and the peripheral adipose tissue of the limbs. Abdominal fat absorbs semaglutide slightly faster during the first 12 to 24 hours post-injection. For individuals sensitive to GLP-1 receptor agonism in the central nervous system, this front-loaded concentration curve frequently correlates with sharp spikes in morning nausea, sulfur burps, and acute fatigue.
Shifting the weekly dose to the outer thigh produces a flatter, slightly prolonged initial uptake curve. Clinical endocrinologists routinely recommend moving away from the abdomen when patients consider discontinuing therapy due to intractable nausea. While overall appetite suppression remains potent across the week, the blunted initial peak often softens severe gastrointestinal reactions.
Subcutaneous Delivery Site Comparison
Selecting a target location involves balancing visibility, physical mobility, and sensitivity to systemic side effects.
| Injection Site | Nausea Risk Profile | Self-Administration Ease | Typical Local Reactions |
|---|---|---|---|
| Abdomen | Moderate to High (faster initial uptake spike) | High (direct eye-line, two hands free) | Mild erythema, superficial itching |
| Outer Thigh | Low to Moderate (gradual absorption curve) | High (seated position, clear visibility) | Localized bruising, muscular soreness if pushed too hard |
| Upper Arm | Low to Moderate (steady dispersion) | Low (requires partner or awkward bracing) | Tenderness when lying on arm, contact bruising |
Step-by-Step Injection Mechanics: Eliminating Pain and Bruising
Mechanical errors cause the vast majority of injection site reactions. The standard single-dose autoinjector pen features a concealed, pre-attached needle that fires upon firm downward pressure. Implementing a rigorous routine prevents wasted medication and subcutaneous tissue trauma.
- Temperature Moderation: Injecting semaglutide straight from the refrigerator stings significantly. Pull your pen from cold storage 15 to 30 minutes prior to use, allowing the solution to reach room temperature (between 59°F and 86°F). Do not expose the pen to direct heat or sunlight.
- Inspection: Check the viewing window. The liquid must appear completely clear and colorless. If particles or cloudiness appear, discard the device.
- Skin Preparation: Swab the target surface thoroughly with a 70% isopropyl alcohol pad. Let the skin air-dry completely for 10 to 15 seconds. Injecting through wet alcohol carries the solvent beneath the skin, causing sharp, immediate stinging.
- Positioning and Angle: Hold the autoinjector at a strict 90-degree angle perpendicular to the clean skin surface. Do not pinch the skin if you are using an autoinjector, as pinching alters the built-in depth guard mechanism; simply press down against flat, taut skin. (If drawing manually from Wegovy vials with an ultra-fine insulin syringe, pinching a fatty fold remains recommended).
- The 10-Second Rule: Press the pen firmly downward until the click mechanism triggers. You will hear an initial click indicating the injection has begun, followed by a second click several seconds later. Continue holding the pen firmly against your skin for a full count of 10 seconds after the second click to confirm the yellow plunger bar has completely stopped moving.
- Post-Injection Care: Lift the pen straight up. If a microscopic droplet of blood appears, press gently with a clean cotton ball or gauze. Avoid rubbing or massaging the site, which forces the medication into surrounding capillaries prematurely and increases bruising and skin irritation.
The Site Rotation Technique: Preventing Lipohypertrophy
Repeatedly puncturing the exact same patch of skin creates dense scar tissue beneath the surface, a clinical condition termed lipohypertrophy. These rubbery, fibrotic fat deposits impede systemic drug absorption, leading patients to mistakenly believe their medication has stopped suppressing hunger.
Adopt a systematic site rotation technique. If you choose the abdomen, visualize the space divided into four quadrants centered around your navel: upper right, lower right, lower left, and upper left. Move clockwise by one quadrant each week, keeping every new puncture at least 1 to 1.5 inches away from your previous dose.
The same rule applies to the legs: alternate between the right and left thighs on a bi-weekly cadence. Never inject into skin that is bruised, tender, red, hard, or scarred from previous surgeries or stretch marks.
Pencils, Vials, and Emerging Oral Formulations
The clinical landscape for GLP-1 administration looks markedly different than it did during the drug's initial commercial rollout. The single-dose autoinjector pen remains the primary format across North America, prized for its hidden needle and automatic safety shield. However, high production costs and component supply strain prompted regulatory filings and commercial shifts toward traditional Wegovy vials paired with separate, disposable U-100 insulin syringes.
Using standard vials requires drawing the liquid manually, eliminating mechanical pen-misfire concerns while demanding greater fine-motor dexterity from patients. Concurrently, data on high-dose oral semaglutide alternative tablets shows comparable weight reduction rates without needles. Yet oral semaglutide brings its own rigid rules: swallowing a tablet every single morning with no more than 4 ounces of plain water, waiting 30 minutes before consuming any food, beverages, or other morning medications. For patients unwilling to coordinate morning fasting routines, the weekly subcutaneous injection remains the superior lifestyle option.
Frequently Asked Questions (FAQ)
Q1: What should I do if a small puddle of medicine leaks out after I lift the pen?
A1: A tiny surface bead is normal and represents less than a fraction of a percent of your total dose. However, if liquid runs down your skin, you likely pulled the pen away before the internal plunger completed its cycle. Never administer a second injection to compensate, as this risks accidental overdose. Document the issue, wait for your next scheduled injection day, and maintain firm pressure for a full 10-second hold next time.
Q2: Why does an itchy, red bump form at my injection spot 24 hours later?
A2: Mild localized hypersensitivity is common with peptide therapeutics. It often stems from the skin reacting to the mechanical trauma of the needle or an immune response to the protein formulation. If the redness remains smaller than the size of a quarter and resolves within three days, it is generally harmless. Applying an over-the-counter hydrocortisone cream helps. If swelling expands, feels unusually hot, or is accompanied by systemic hives, contact your prescribing physician immediately.
Q3: Can I inject Wegovy into my upper arm by myself?
A3: Self-administering into the upper arm is technically possible by pressing the autoinjector down while bracing the back of your arm against a doorframe or the back of a firm chair to bunch up the tricep fat. However, this awkward angle raises the risk of slipping and bending the internal needle. Unless an assistant or caregiver is available to deliver the dose, the abdomen or thigh offers far more reliable control.
Q4: Does injecting into stomach fat burn belly fat specifically?
A4: No. Subcutaneous semaglutide operates systemically, entering your bloodstream to target appetite receptors in the hypothalamus and slow gastric motility in the digestive tract. It does not provide localized lipolysis or "spot reduction." Fat loss occurs uniformly across the entire body based on overall caloric deficit, genetics, and metabolic rate, regardless of which approved site you choose.
Establishing Long-Term Injection Consistency
Navigating chronic GLP-1 therapy requires treating the weekly administration as a precise clinical task rather than an afterthought. If nausea regularly impairs your productivity or well-being during the first 48 hours following a dose, pivot your site selection directly to the outer thigh. Keep track of each injection spot in a personal log, verify the liquid clarity through the inspection window, and allow the solution to come up to room temperature to mitigate discomfort. With a methodical approach to rotating sites and managing the physical injection mechanics, subcutaneous semaglutide becomes a quick, painless, and sustainable weekly habit.