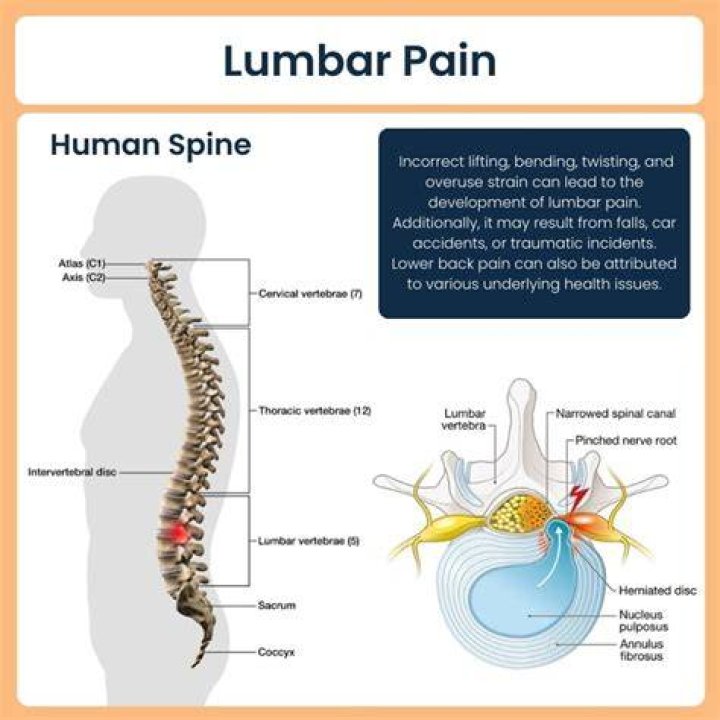
Are White Lip Bumps Contagious? Dermatologists Fact-Check the 6 Common Causes

A sudden pale speck on your lip line can trigger instant anxiety. When people spot unexpected white zits on lips, their immediate impulse is often dread, assuming every pale lesion is an incurable viral outbreak. Panic-driven searches flood forums, where terrified individuals confuse normal anatomical structures with infectious pathogens.
Just as digital newsrooms trace how rapidly unverified rumors explode during breaking events, a dynamic examined in a forensic WYFF Report on digital misdirection, medical communities battle an endless stream of lip-care misinformation. Board-certified dermatologists encounter this anxiety daily. The reality is far less alarming: the vast majority of small white spots on the mouth are benign, non-transmissible, and entirely manageable.
📌 Key Takeaways:
- Transmission Reality: Over 85% of white lip spots stem from non-contagious origins like ectopic glands, trapped keratin, or blocked pores.
- The Viral Marker: Only herpes simplex virus type 1 produces transmissible sores, identifiable by tingling prodrome pain and clustered fluid vesicles.
- Treatment Caution: Applying aggressive facial acne products directly to mucosal lip skin frequently induces severe contact cheilitis rather than clearing the bump.
The Anatomy of the Vermilion Border and Why Bumps Form
The lips occupy a delicate transition zone between two distinct tissue systems. On the outside sits stratified squamous keratinized skin equipped with hair follicles and sweat glands. On the inside lies moist oral mucosal membrane. The distinct line separating these two zones is the vermilion border.
Because this margin lacks the protective thickness of standard facial skin, any minor alteration beneath the surface becomes visible instantly. While ordinary facial skin houses hair follicles that allow sebum to drain freely, the lips do not produce typical hair growth. When clogged sebaceous glands or trapped keratinocytes develop along this border, they have nowhere to go. They push upward against the semi-translucent skin, reflecting light as tiny white, cream, or yellowish bumps.
The Non-Contagious Majority: Fordyce Spots, Milia, and Mucoceles
Clinical data shows that Fordyce spots represent the single most common cause of pale lip bumps, occurring in roughly 70% to 80% of adults. These are not infections or diseases. They are ectopic sebaceous glands, normal oil-producing glands located where hair follicles are absent. Fordyce spots present as painless, pinpoint granules (1, 2 millimeters across) along the outer lip margin. They become noticeably pronounced when you stretch the lip taut. They never spread to other people and require no medical intervention.
A second common culprit is milia. These are tiny, stubborn epidermal cysts filled with laminated keratin rather than sebum. Milia arise when dead skin flakes fail to slough away, becoming encapsulated just beneath the lip edge. Unlike true acne blemishes, milia lack a central pore and cannot be extracted through manual squeezing.
Trauma to the mouth introduces a third benign condition: the mucous retention cyst, or mucocele. When someone accidentally bites their inner lip or damages a microscopic salivary duct, saliva leaks into the surrounding connective tissue. The resulting pool forms a smooth, dome-shaped swelling that often appears translucent, bluish, or pale white. While they can grow up to a centimeter in size, mucoceles are completely sterile and harmless.
Lip Pimples vs Herpes: Identifying HSV-1 Before It Spreads
The primary concern behind most searches is the fear of cold sores, triggered by herpes simplex virus type 1 (HSV-1). Distinguishing between isolated comedones and viral blisters is critical for personal comfort and stopping disease transmission.
The distinction lies in chronology and sensation. A standard lip pimple develops silently within an oil duct near the vermilion border. It forms a solitary, firm whitehead with mild local tenderness when pressed. In stark contrast, an HSV-1 outbreak announces itself 24 to 48 hours before any physical bump emerges. Patients experience a distinct prodrome characterized by localized tingling, burning, or throbbing.
When the viral lesion appears, it does not present as a firm whitehead. Instead, it erupts as a tight cluster of small, clear, fluid-filled vesicles resting on an erythematous (red, inflamed) base. Within two to three days, these fragile vesicles rupture, weep contagious viral fluid, and form a honey-colored crust. True pimples never weep clear fluid across clustered surfaces or form this characteristic scab.
Dermatological Comparison: Six Distinct Causes of White Lip Spots
To assist in symptom differentiation, clinical presentations across the six most prevalent lip lesions show marked variations in etiology, transmissibility, and intervention:
| Clinical Condition | Visual & Sensory Characteristics | Contagious? | Standard Management |
|---|---|---|---|
| Fordyce Spots | Uniform 1, 2 mm yellowish-white granules; painless; visible on stretching. | No | No treatment needed; optional pulse dye or CO2 laser for cosmetic removal. |
| Cold Sores (HSV-1) | Tingling prodrome; clustered fluid-filled blisters that rupture and crust over. | Highly Contagious | Oral antivirals (valacyclovir) within 48 hours; topical docosanol. |
| Milia | Hard, solitary, pearly white keratin domes; no central pore; non-tender. | No | In-office sterile lancing; gentle topical retinoids (avoiding lip interior). |
| Comedones (Acne) | Single raised whitehead on facial hair edge; mild inflammation; central plug. | No | Targeted spot treatments; non-comedogenic balms; warm compresses. |
| Oral Thrush | Creamy white cottage-cheese plaques; raw, red, bleeding surface when scraped. | Low (Opportunistic) | Prescription oral antifungal suspensions (nystatin) or oral fluconazole. |
| Mucous Retention Cyst | Smooth, soft, fluid-filled nodule on inner lip mucosa; bluish to pale hue. | No | Surgical excision, cryotherapy, or marsupialization if persistent. |
Treatment Protocols: When Topical Salicylic Acid Helps and When It Harms
Home-treatment mistakes routinely turn microscopic spots into full-blown dermatological emergencies. When an individual presumes a bump is a standard zit, they reach for concentrated acne washes. Applying aggressive topical salicylic acid or high-strength benzoyl peroxide directly onto mucosal margins dissolves the fragile epithelial lipid barrier within hours.
The result is contact cheilitis: a painful, red, peeling inflammatory reaction that leaves lips cracked, burning, and prone to secondary bacterial infection. Salicylic acid spot treatments belong solely on keratinized facial skin outside the vermilion border. They should never touch the red lip surface.
Similarly, attempting to squeeze or pop white lip bumps creates severe tissue trauma. Squeezing a Fordyce spot causes bruising and scarring of healthy sebaceous tissue. Puncturing a mucocele simply causes the salivary pool to refill while increasing infection risks. Squeezing an active HSV-1 blister releases millions of infectious virions, potentially spreading the herpes virus to fingers (herpetic whitlow) or surrounding facial regions.
Another condition frequently mistaken for white zits is oral thrush, caused by an overgrowth of Candida albicans. Unlike isolated bumps, thrush forms diffuse, velvety white patches along the inner lips, tongue, and corners of the mouth (angular cheilitis). If you attempt to wipe these plaques away with a swab, they leave behind an irritated, bleeding red patch. Thrush demands prescription antifungal therapy, not cosmetic skin washes.
When to Seek Professional Dermatologist Diagnosis
While the overwhelming majority of pale spots are harmless, self-diagnosis carries clinical limits. Persistent, non-healing lip lesions require a formal dermatologist diagnosis to rule out rare but serious conditions such as actinic cheilitis (a precancerous change caused by chronic ultraviolet exposure) or squamous cell carcinoma.
Schedule an evaluation if you notice any of the following clinical warning signs:
- A firm, scaly white or red nodule that fails to heal after 14 consecutive days.
- Lesions that ulcerate, bleed spontaneously, or feel hardened (indurated) beneath the surface.
- Rapidly spreading white plaques inside the mouth accompanied by painful swallowing.
- Unexplained localized numbness or loss of sensation across the lower lip.
Dermatologists use non-invasive dermoscopy, viral swabs, and targeted biopsies to identify underlying pathologies within minutes, saving patients months of misplaced anxiety.
Frequently Asked Questions (FAQ)
Q1: Can I squeeze or pop white spots on my lip if they look like pimples?
A1: Never squeeze white bumps on the lip. If the spot is a Fordyce gland or milia, squeezing will cause scar tissue and capillary damage without dislodging the bump. If the lesion is a viral cold sore, popping it spreads infectious fluid across your face and can cause severe secondary bacterial infections.
Q2: How can I tell whether a white bump is a pimple or an early cold sore?
A2: True pimples appear as solitary plugs along the outer skin border without advance warning. Cold sores typically begin with 24 to 48 hours of localized tingling, itching, or burning, followed by a tight cluster of multiple clear blisters on an inflamed red base that burst and crust over.
Q3: Will Fordyce spots ever go away permanently on their own?
A3: Fordyce spots do not disappear on their own because they are natural anatomical oil glands. They are completely harmless and pose no medical danger. If they present cosmetic concerns, dermatologists can reduce their visibility using specialized vascular lasers, micro-punch excision, or mild chemical peels.
Navigating Lip Health with Clinical Precision
Discovering a pale spot along your lip line is startling, but panic is almost never warranted. True viral infections present with unmistakable warning signs, burning sensations, clustered blistering, and systemic crusting. When a spot is isolated, asymptomatic, and stable, it is almost certainly a normal structural variant like a Fordyce gland, trapped keratin, or a minor clogged follicle.
Avoid harsh chemical exfoliants and the urge to pick at delicate mucosal tissue. Treating the mouth requires patience, gentle barrier creams, and accurate diagnostic assessment. When doubt lingers beyond two weeks, stepping into a clinical office delivers definitive clarity, dispelling viral fears with verifiable medical science.